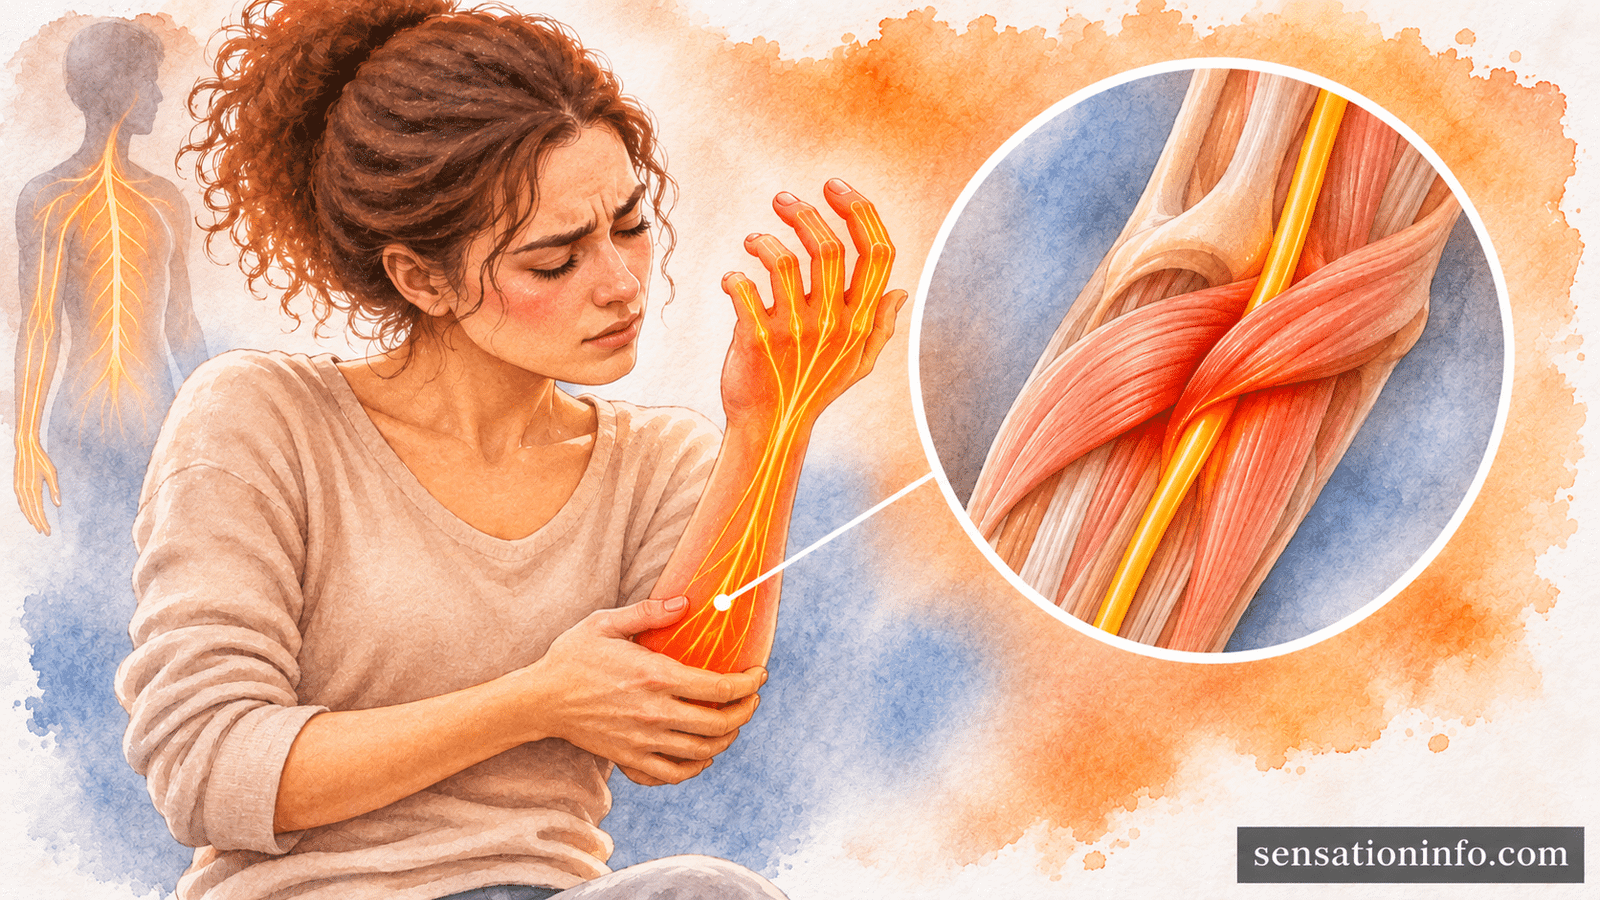

Pronator teres syndrome happens when the median nerve gets squeezed in your upper forearm, just below the elbow, causing an aching forearm and tingling in the thumb, index, and middle fingers. Because the hand symptoms look so much like carpal tunnel syndrome, it is one of the most commonly missed nerve problems in the arm.
Many patients reach me after months of wrist splints, or even wrist surgery, that never touched the real problem. Once the right spot is found, most people improve with rest, therapy, and changes to how they use the arm.
Why Do My Forearm and Hand Hurt at the Same Time?
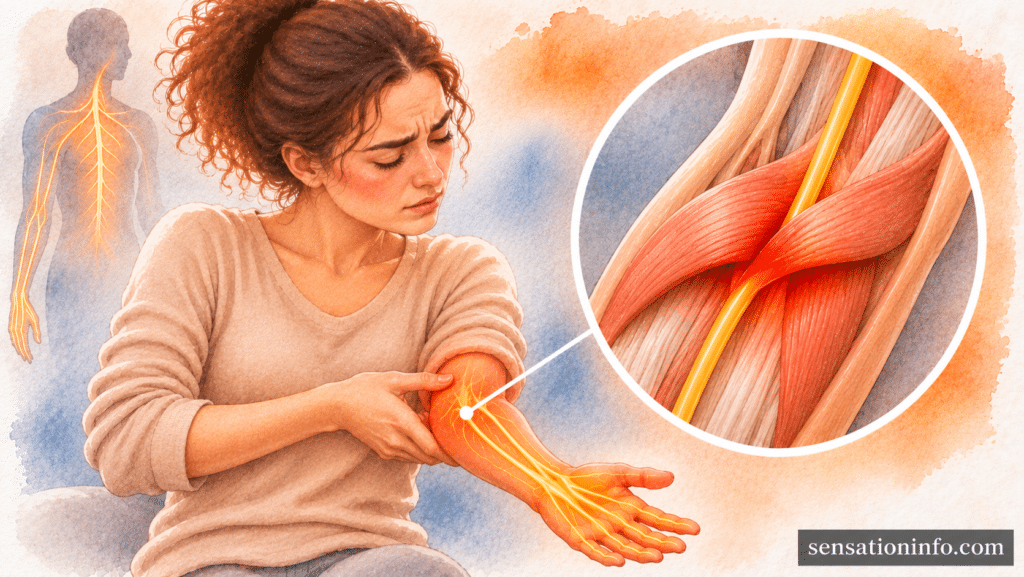
Your forearm aches and your fingers tingle because one nerve is being pinched higher up than most people expect. The pressure point sits in the forearm, but the median nerve carries the symptoms all the way to your hand.
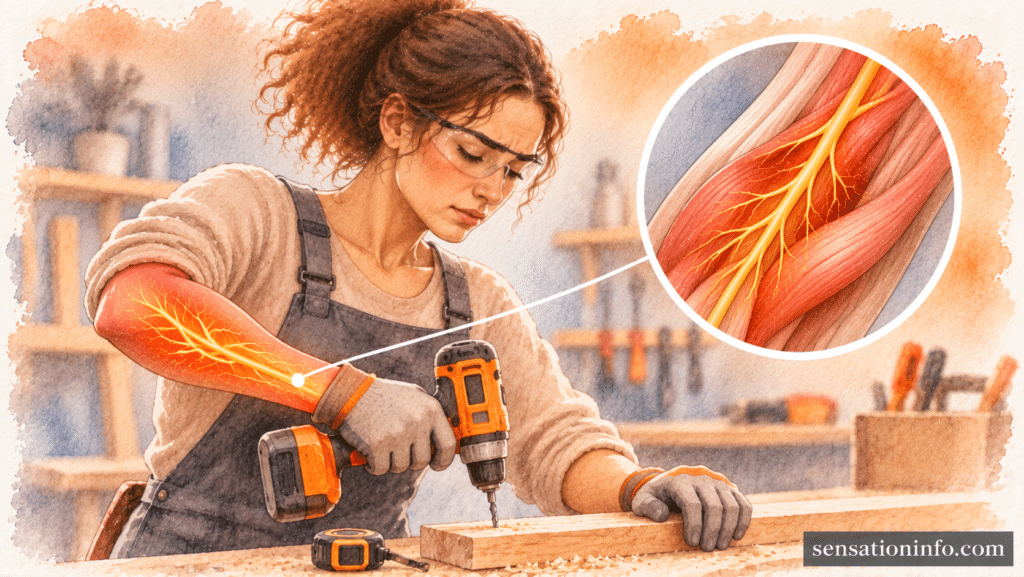
The median nerve runs from your neck down the inside of your arm. Just past the elbow, it passes between the two heads of the pronator teres, the muscle that turns your palm to face down.
When that muscle is overworked, thickened, or tight, it can press on the nerve, a problem doctors call median nerve entrapment. Nearby bands of tissue can add to the squeeze, including the lacertus fibrosus, a tough sheet of tissue from the biceps tendon, and a fibrous arch on a deeper forearm muscle.
Pronator teres syndrome, also called pronator syndrome, is a pinched median nerve in the forearm, not the wrist, which is why wrist treatments often fail to fix it.
What Does Pronator Teres Syndrome Feel Like?
Most people describe a deep, dull ache in the upper forearm, along with tingling or numbness in the hand. The ache usually builds through the day as you use the arm.
When I take a history, these are the complaints I hear most often. If several of them sound familiar, write them down before your appointment, because the pattern matters more than any single symptom.
- A tired, aching feeling in the front of the forearm, below the elbow crease
- Tingling or numbness in the thumb, index finger, middle finger, and half of the ring finger
- Numbness in the palm itself, not just the fingers
- A weaker grip, dropping things, or trouble with jar lids and childproof caps
- Symptoms that get worse with gripping or twisting and ease with rest
Night symptoms are less typical here. If your hand wakes you at night, your doctor will think harder about the wrist.
Which Activities Make It Worse?
Repeated twisting of the forearm combined with a firm grip is the classic trigger, a type of repetitive strain. Anything that turns your palm down against resistance makes the pronator teres work hard and squeeze the nerve.
Patients are often surprised by how ordinary their triggers are. These are the activities I ask about, because changing them is a big part of getting better.
- Using screwdrivers, wrenches, or hammers, especially for hours at a time
- Assembly line or factory work with repeated forearm rotation
- Weightlifting, particularly curls and pressing movements, and racquet sports or rowing
- Playing an instrument such as violin or guitar for long sessions
- Long gaming or computer sessions with a tight grip on a controller or mouse
Long hours with a controller can also leave the forearm sore, and burning forearm pain from gaming is often the first sign the muscles are overloaded.
Is It Pronator Teres Syndrome or Carpal Tunnel?
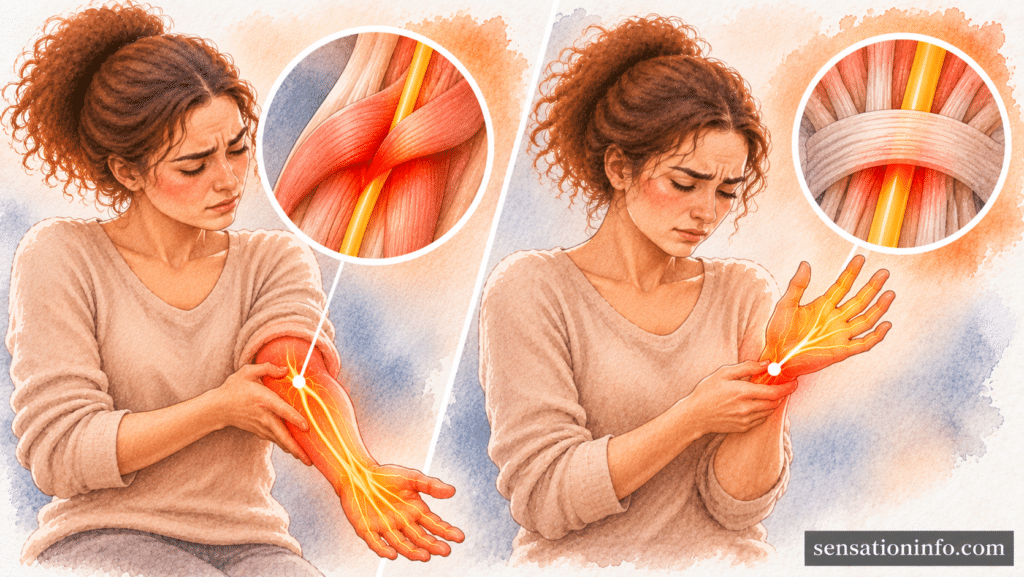
Both conditions pinch the same median nerve, so the finger symptoms overlap. The differences show up in where the pain is, when it happens, and whether the palm goes numb.
This is the comparison I walk through when a patient asks why their carpal tunnel treatment did not work. Use it to describe your own pattern to your doctor.
| Feature | Pronator teres syndrome | Carpal tunnel syndrome |
|---|---|---|
| Where the nerve is pinched | Upper forearm, just below the elbow | Wrist |
| Main pain | Aching in the upper forearm | Wrist and hand, sometimes up the forearm |
| Palm numbness | Often present | Usually spared |
| Night symptoms | Uncommon | Very common, often wakes you |
| Made worse by | Twisting the forearm and gripping | Bending the wrist, holding a phone, driving |
| Tender spot | Upper forearm muscle | Front of the wrist |
| Nerve conduction study | Often normal | Usually shows slowing at the wrist |
The two can also happen together. In one surgical series of people treated for forearm median nerve compression, nearly half had already had carpal tunnel surgery that did not relieve their symptoms.
If your thumb and index finger numbness came back after wrist surgery, or never improved, ask your doctor to examine the forearm as well.
What Else Could Cause Forearm Pain and Hand Tingling?
Several nerve and muscle problems cause similar symptoms, and the details help sort them out. The table below shows the patterns I look for when a patient comes in with an aching forearm or tingling hand.
Match what you feel to the closest row, then check how soon you should be seen. Remember that two problems can exist at the same time.
| Where it is | What it feels like | What comes with it | Likely cause | How urgent |
|---|---|---|---|---|
| Upper forearm ache, tingling thumb to ring finger, palm numb | Dull ache, pins and needles | Worse with twisting and gripping, rarely at night | Pronator teres syndrome | Doctor visit within a few weeks |
| Thumb, index, and middle fingers, palm spared | Tingling, fingers “asleep” | Wakes you at night, eased by shaking the hand | Carpal tunnel syndrome | Doctor visit within a few weeks |
| Little finger and half the ring finger | Numbness, tingling | Worse with the elbow bent, weak pinch | Cubital tunnel syndrome | Doctor visit within a few weeks |
| Whole arm or the pinky side of the hand | Aching, heaviness, tingling | Worse with arms overhead, neck or shoulder pain | Thoracic outlet syndrome | Doctor visit within a few weeks |
| Thumb and index finger, with neck pain | Shooting or burning pain | Pain from the neck down the arm | Pinched nerve in the neck (cervical radiculopathy) | Doctor visit within 1 to 2 weeks |
| Inner elbow bump, pain into the forearm | Sore, achy | Pain with gripping, no numbness | Golfer’s elbow (medial epicondylitis) | Routine visit if not better in a few weeks |
When tingling settles in the little and ring fingers instead, cubital tunnel syndrome at the elbow is the more likely cause. If your whole arm aches when you reach overhead, thoracic outlet syndrome near the collarbone deserves a look.
Still unsure which nerve fits your symptoms? Our nerve symptom checker can help you narrow it down before your visit.
What Will My Doctor Check at the Appointment?
Pronator teres syndrome is mainly diagnosed through your story and a careful hands on exam. Tests help rule out other problems, but they often look normal in this condition.
I start with questions, because your answers point me to the right spot along the nerve. Thinking about these beforehand will make your visit far more useful.
- Where does the ache sit, and where does the tingling go?
- Does your palm go numb, or only your fingers?
- Which tasks bring it on, and how long until it eases?
- Does it wake you at night?
- Have you had wrist splints, injections, or carpal tunnel surgery already?
During the exam, your doctor may press on the upper forearm to see whether it brings on tingling, and ask you to turn your palm down while they resist. They may also tap along the nerve in the forearm and check your grip and pinch strength.
A nerve conduction study is often normal in pronator teres syndrome. A normal result does not rule it out; the test mainly checks the wrist and neck, while ultrasound or MRI can sometimes show where the nerve is squeezed.
How Is Pronator Teres Syndrome Treated?
Most people get better without surgery. Treatment starts by taking pressure off the nerve and calming the overworked forearm muscles.
The first step is usually rest from the activity that triggers symptoms, along with changes to how you grip and twist. A hand or physical therapist can teach gentle stretches, strengthening, and nerve gliding exercises, which help the nerve move freely through the forearm.
For pain, nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen (Advil) or naproxen (Aleve) can help for a short time. Ask your doctor before using them for more than a few days, especially if you have stomach, kidney, or heart problems.
Some doctors add a brace that limits forearm rotation, or a corticosteroid injection near the tight muscle, which can also help confirm the diagnosis.
Surgery is considered when symptoms persist after about six months of good nonsurgical care. The surgeon releases every tight structure pressing on the nerve in the upper forearm, not just one. Before agreeing, ask your surgeon how long recovery takes and whether your wrist needs treatment too.
What Can I Change at Work and at Home?
Small changes to how you use your arm can take a lot of pressure off the nerve. These are the adjustments I suggest most often while treatment takes effect.
Try them for a few weeks and note which ones help. Your therapist can tailor them to your job or sport.
- Break up repetitive tasks. Rotate between different jobs, and rest your forearm every 30 to 60 minutes.
- Use power tools when you can. A cordless screwdriver spares your forearm hundreds of twists.
- Loosen your grip. Use thicker handles and avoid squeezing tools, rackets, or controllers harder than needed.
- Adjust your workouts. Cut back on curls and heavy pressing until symptoms settle, and work with a trainer on form.
When Should I See a Doctor?
Pronator teres syndrome is not an emergency, but ongoing symptoms deserve a visit. A few signs, though, point to something that needs faster care.
These situations need urgent help. Do not wait to see whether they pass.
- Sudden arm numbness or weakness with face drooping or slurred speech: Call 911. These are warning signs of a stroke.
- Rapid, painful swelling of the forearm after an injury, or while taking a blood thinner: Go to the emergency room the same day, because bleeding can press on the nerve.
These signs are not emergencies, but they need a prompt doctor visit. They suggest the nerve is under more pressure or that another problem is involved.
- Tingling or ache that lasts more than 2 weeks despite rest
- A weaker grip, dropping things, or trouble pinching
- Numbness that keeps spreading or affects both hands
- Symptoms that came back after carpal tunnel surgery
- Neck pain that shoots down the same arm
How Long Does Pronator Teres Syndrome Take to Heal?
With rest, therapy, and activity changes, many people notice improvement over several weeks to a few months. The longer the nerve has been squeezed, the slower recovery tends to be.
After surgery, the ache often eases before the tingling does, and daily tasks usually return well before heavy lifting or full sports.
Key Takeaways
Here is what matters most if your forearm aches and your fingers tingle. Each point stands on its own, so you can return to it when you need a reminder.
- Pronator teres syndrome is a pinched median nerve in the upper forearm that causes forearm aching and tingling in the thumb, index, and middle fingers.
- Palm numbness, forearm pain, and symptoms during the day rather than at night point toward the forearm instead of the wrist.
- Repeated twisting and gripping, from tools, sports, instruments, or gaming, is the most common trigger.
- Nerve conduction studies are often normal, so diagnosis relies on a careful history and exam.
- Most people improve with rest, therapy, and activity changes, and surgery is considered only after months of good nonsurgical care.
Frequently Asked Questions
Pronator teres syndrome often improves when the activity that triggers it is reduced, especially if it is caught early. Most people need some combination of rest, therapy, and changes to how they grip and twist, and symptoms that last more than a few weeks should be checked by a doctor.
Pronator teres syndrome and golfer’s elbow are different conditions that can occur together. Golfer’s elbow is irritation of the tendons at the inner elbow and does not cause hand numbness, while pronator teres syndrome is a pinched median nerve that causes forearm aching and tingling in the thumb, index, and middle fingers.
Hand tingling can continue after carpal tunnel surgery when the median nerve is also squeezed higher up in the forearm, as in pronator teres syndrome. A doctor can examine the forearm, neck, and wrist to find whether a second pressure point is involved.
Doctor’s Recommendation
When forearm and hand symptoms keep returning, the next clinical question is whether the wrist, the forearm, or the neck is involved, and often more than one. Understanding what a nerve conduction study can and cannot show helps you prepare for testing and make sense of your results with your doctor.
References
- El-Haj M, Ding W, Sharma K, Novak C, Mackinnon SE, Patterson JMM. Median Nerve Compression in the Forearm: A Clinical Diagnosis. Hand (N Y). PubMed Central, National Library of Medicine. 2021.
- Mayo Clinic. Carpal tunnel syndrome: Symptoms and causes. Mayo Clinic. 2026.
- Cleveland Clinic. Carpal Tunnel Syndrome. Cleveland Clinic. Accessed 2026.
- Cleveland Clinic. Cervical Radiculopathy (Pinched Nerve). Cleveland Clinic. Accessed 2026.
- Centers for Disease Control and Prevention. Signs and Symptoms of Stroke. CDC. Accessed 2026.